

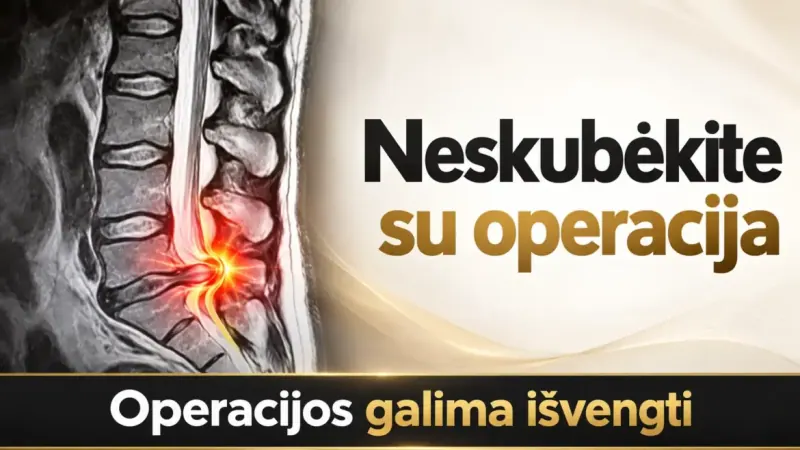
Urgent surgery is needed when a herniation causes cauda equina syndrome or rapidly worsening leg weakness. Otherwise, treatment without surgery usually comes first, and surgery is considered if severe leg pain persists despite several months of treatment.
What is an L5–S1 herniation
L5–S1 is the last lumbar vertebra (L5) and the first sacral vertebra (S1). The disc between them carries the greatest load, which is why herniations are most common here. When the disc's outer ring tears, part of the core pushes out and can press on the S1 nerve root.
Symptoms
Irritation of the S1 nerve root has a fairly typical pattern:
- pain runs through the buttock, the back of the thigh and calf to the outer edge or sole of the foot;
- the little toes or the outer edge of the foot feel numb;
- it is hard to rise onto your toes on the affected leg;
- pain gets worse when sitting, coughing or sneezing.
When surgery is urgent
Do not wait – call 112 or go to A&E if:
- your groin or inner thighs are numb (the "saddle" area);
- you have problems passing urine or controlling your bowels;
- your leg is getting weaker within hours or days, or your foot starts to drop.
This may be cauda equina syndrome. It needs surgery as soon as possible, otherwise nerve damage may become permanent.
When planned surgery is considered
Without urgent signs, surgery is usually considered when:
- severe leg pain persists despite several months of proper treatment;
- the pain is so strong that you cannot work, sleep or walk, and it is not easing;
- muscle weakness persists or gets worse.
The decision about surgery is made by a neurosurgeon who assesses your symptoms and MRI together.
Treatment without surgery
For many patients, symptoms ease within weeks or months as inflammation settles and the body gradually reabsorbs part of the herniated disc tissue. Treatment aims to reduce pain and pressure on the nerve while this happens, and to restore movement.
- Spinal decompression reduces pressure on the disc and nerve root.
- Manual therapy and nerve mobilisation improve mobility and how the nerve glides through tissue.
- High-intensity laser reduces inflammation and pain signals.
- Exercises strengthen the deep muscles and help prevent a recurrence.
What an MRI shows
An MRI shows the size and direction of a herniation and whether it actually presses on a nerve. But the image does not always match the symptoms: sometimes a large herniation causes little pain, and a small one causes a lot. That is why decisions are based on the MRI and examination together.
At our clinic, treatment starts only after your MRI is assessed: the specialist reviews the scan, compares it with the examination and builds your treatment plan. How we assess your MRI
What to do now
- Check for urgent warning signs. If you have any, call 112.
- Stay as active as the pain allows. Long bed rest usually does not help.
- Avoid lifting heavy objects and sitting for long periods without breaks.
- Get an MRI, or bring the one you have to your consultation.
- See a specialist who can assess whether treatment without surgery is right for you.

This article is for information only and does not replace a consultation with a doctor.